ME Hoffman, R Abuatiq, K Bokowy, AL Fiss, J Looper, KM Steele (2026) “Up and down: analyzing physical activity and posture with wearable sensors during partial bodyweight supported play for young children with down syndrome”

Journal Article in Developmental Neurorehabilitation

Children with Down syndrome commonly experience delays in motor milestones, such as pulling to stand and walking, due to musculoskeletal factors associated with DS like hypotonia and ligament laxity

Aim: Understanding how to support age-appropriate motor exploration while increasing movement, physical activity and upright time is essential for optimizing developmental and health outcomes in young children with Down syndrome. Open-area partial bodyweight support (PBWS) systems can help support motor development, but no study has objectively reported motor behavior changes, such as increased leg activity or time spent upright.  

Methods: This randomized, multisite crossover trial included children with Down syndrome who could sit independently but were not yet walking. Each child completed nine 30-minute play-based sessions with and without PBWS. Physical activity and posture were measured using shank-worn accelerometers, capturing the percentage of time spent in high physical activity and upright. Nonparametric Mann-Whitney U tests compared outcome measures between PBWS and non-PBWS conditions.

Results: Fifteen children (mean age: 19.4 months, range: 12–31 months) completed study procedures. Across all participants, high physical activity did not noticeably increase from the first to last session. The median change was −5.0% (IQR: −13.4- +9.05%) with PBWS and −2.53% (IQR: −13.7- +12.9%) without PBWS. Time spent on feet showed a median increase of +2.38% with PBWS (IQR: −0.96 – +12.24) and a decrease of −1.08% without PBWS (IQR: −7.70 - + 1.02%). A statistically significant difference between conditions (p = .042) indicated greater improvements in time on feet during PBWS sessions versus without.

Interpretation: PBWS did not increase time spent in high physical activity, but did support increased upright posture over time. These findings suggest PBWS systems may provide a supportive environment for practicing upright postures in early motor development for children with Down syndrome.
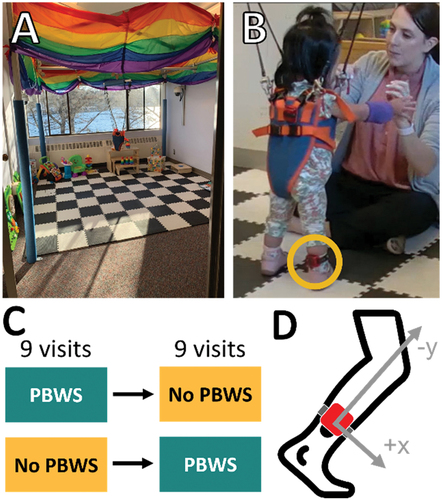
(A) The enriched exploratory play space with the PBWS system (B) Actigraph GT3X+ triaxial accelerometers were placed on a child’s right shank. (C) This study used a randomized crossover study design. Nine children had PBWS assistance first, and 6 children second. Each intervention period lasted 3 weeks. (D) The accelerometers were used to calculate physical activity and upright posture.

HA Feldner, K Keithley, KA Ingraham, A Fragomeni, N Zaino, A Sinclair, AN Meltzoff, PK Kuhl, KM Steele (2026) “Learning powered mobility: caregiver perceptions of young children’s capabilities and device impact”

Journal Article in Disability and Rehabilitation: Assistive Technology

Self-initiated mobility experiences are critical for young children with disabilities and may be augmented through powered mobility.

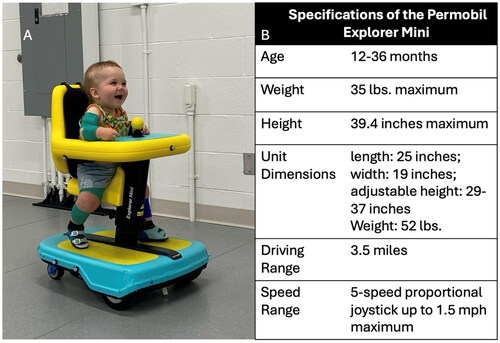
(A) A child participant driving the Permobil ® Explorer Mini (photo courtesy of the IMPACT Collaboratory). (B) Specifications of the Explorer Mini device.

Aim: The purpose of this study was to understand caregiver perceptions of powered mobility intervention following a 12-session trial of a novel powered mobility device.  

Methods: Ten caregivers (4 M/6F) of children with cerebral palsy (Gross Motor Function Classification System IV-V) and other developmental disabilities (21.8 ± 5.9 months). Children participated in 12 in-lab driving sessions (exploratory or goal directed) using the Explorer Mini (Permobil AB, Sweden). Exit interviews were conducted with caregivers at the final visit, transcribed verbatim, coded inductively, and analysed until themes emerged.

Results: Four themes emerged from the data: (1) Changing views of capability and adaptability; (2) Emerging autonomy; new skills in and out of the device; (3) Clear need and benefit with some drawbacks; and (4) Lingering stigma and uncertainty 

Interpretation: PM trial positively shifted caregiver’s perceptions of both PM in general and their child’s capabilities, with a desire for greater access to PM at home to support development. These beliefs remained juxtaposed with lingering stigma for some caregivers about PM devices, and a stated desire for more modifiable PM options for children with different positioning or access needs.

AK Clarke, AJ Ries, MH Schwartz, KM Steele (2026) “Influence of body weight support on motor control in typically developing children and children with cerebral palsy”

Journal Article in Journal of Biomechanics

For children with cerebral palsy (CP), interventions that provide support like BWS treadmill training, orthoses, or walkers have been shown to improve walking speed, endurance, and/or kinematics – although responses are variable and challenging to predict.

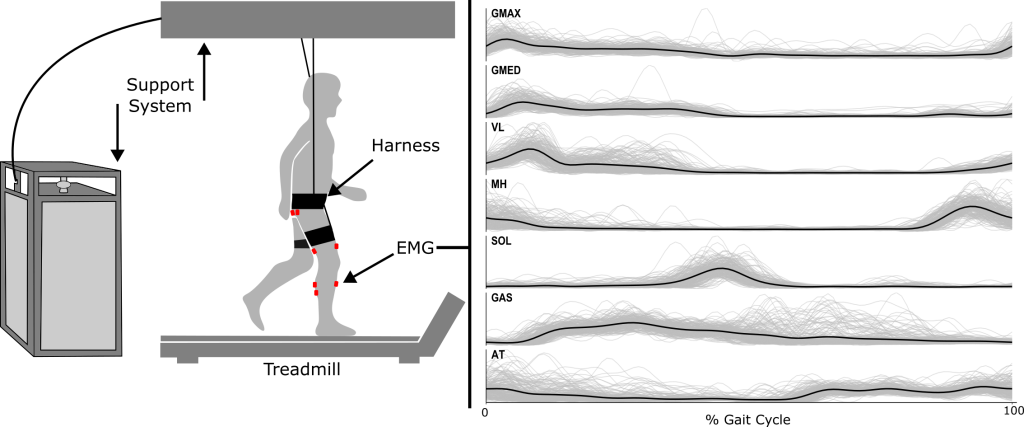
Experimental setup. Body weight support is provided via vertical force application at the pelvis by the support system (Humotech, force controller, and overhead gantry). Electromyography was recorded bilaterally from seven lower limb muscles.

Aim: Body weight support (BWS) is often provided during rehabilitation interventions or activities of daily living with assistive devices for children with cerebral palsy (CP). How individuals alter their muscle activity and coordination in response to BWS provides insight into neuromuscular control and may inform the design of future interventions.

Methods: Children with CP (n = 12) and typically developing (TD) peers (n = 8) walked on a treadmill with 1%, 20%, 40%, and 60% BWS while electromyographic (EMG) data was recorded from 7 lower limb muscles. We computed muscle synergies from the EMG data using non-negative matrix factorization.

Results: As BWS increased, activity of support muscles like the gluteus maximus and gluteus medius decreased for both CP and TD groups. Children with CP had significantly reduced synergy complexity compared to TD peers (total variance accounted for by one synergy, tVAF1 = 76.3 for CP versus 67.4 for TD averaged across all conditions). However, synergy complexity did not change with BWS for either group.

Interpretation: Although BWS may assist mobility by reducing demand on support muscles, it does not directly modulate motor control.

PK Gill, JM Donelan, KM Steele, MH Schwartz, AJ Ries (2025) Quantifying altered oxygen kinetics and reducing metabolic test times for children with cerebral palsy: a dual-exponential Bayesian modeling approach

Journal Article in Journal of Applied Physiology

Prior research using indirect calorimetry has shown that children with cerebral palsy (CP) exhibit significantly increased energetic costs during walking. However, metabolic testing to obtain oxygen cost is challenging. As a result, differences in oxygen uptake kinetics (V̇o2) in CP compared with their typically developing peers remain unexplored. Step changes in work rate have been shown to result in an exponential V̇o2 response with three distinct phases 1) cardiodynamic, 2) primary, and 3) steady-state.

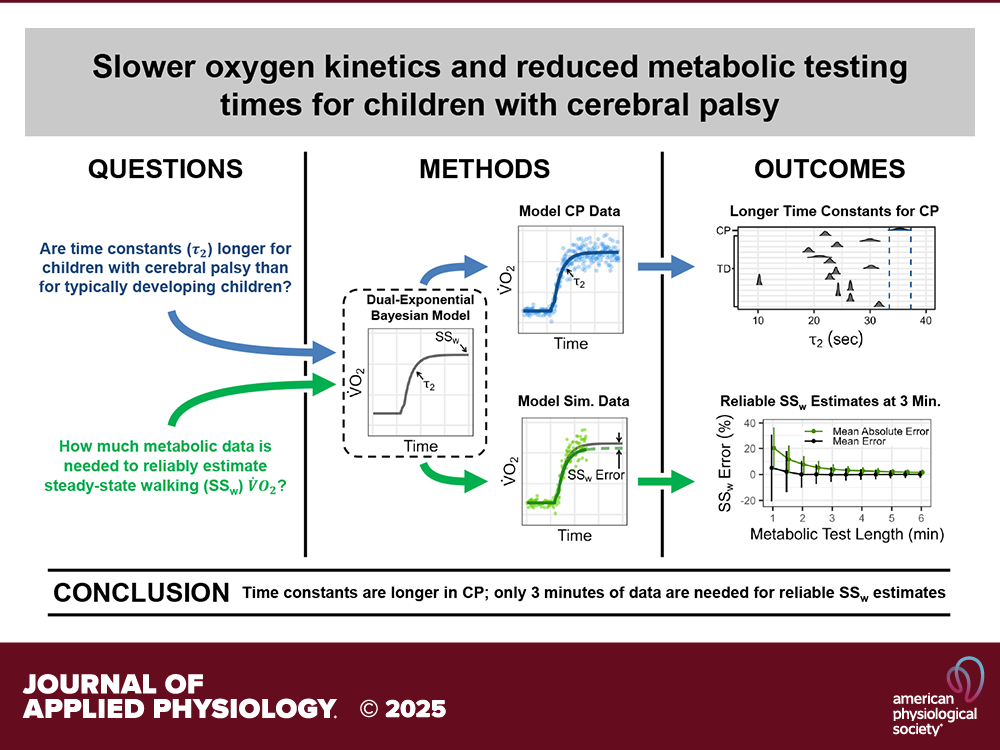
Infographic titled “Slower oxygen kinetics and reduced metabolic testing times for children with cerebral palsy.” The conclusion states "“Conclusion: Time constants are longer in CP; only 3 minutes of data are needed for reliable steady- state walking estimates.Aim: This study aimed to apply a dual-exponential Bayesian model to assess the time constant of the primary phase V̇o2 response from resting to walking in children with CP. In addition, evaluate the model’s ability to estimate steady-state V̇o2 using shorter test durations.

Methods: A dual-exponential Bayesian model was applied to metabolic data from a sample of 263 children with CP. The model estimated the time constant of the primary phase V̇o₂ response and tested the accuracy of steady-state V̇o₂ estimation using only the first 3 minutes of data, compared to the standard 6-minute duration.

Results: The median V̇o2 time constant was 33.1 s (5th–95th percentile range: 14.5–69.8 s), significantly longer than reported values for typically developing children (range of means: 10.2–31.6 s). Furthermore, the model accurately estimated steady-state V̇o2 using only the first 3 min of metabolic data compared with the typical 6 min used in current clinical practice. The 3-min estimate explained >95% of the 6-min estimate variance, with <5% mean absolute error.

Interpretation: Slower oxygen kinetics in children with CP suggest impairments in metabolic control, potentially contributing to their higher energy demands. Although the exact mechanisms remain unclear, this study provides valuable insights into the walking energetics of children with CP and presents a more efficient method for analyzing V̇o2 for this population.

MN Pitts, MR Ebers, CE Agresta, KM Steele (2025) Evaluating Sparse Inertial Measurement Unit Configurations for Inferring Treadmill Running Motion

Journal Article in Sensors

 Inertial measurement units (IMUs) are used to analyze running performance. While leveraging one sensor to estimate kinematic and kinetic variables is common, sparsity limits the number of digital biomarkers that can be evaluated.

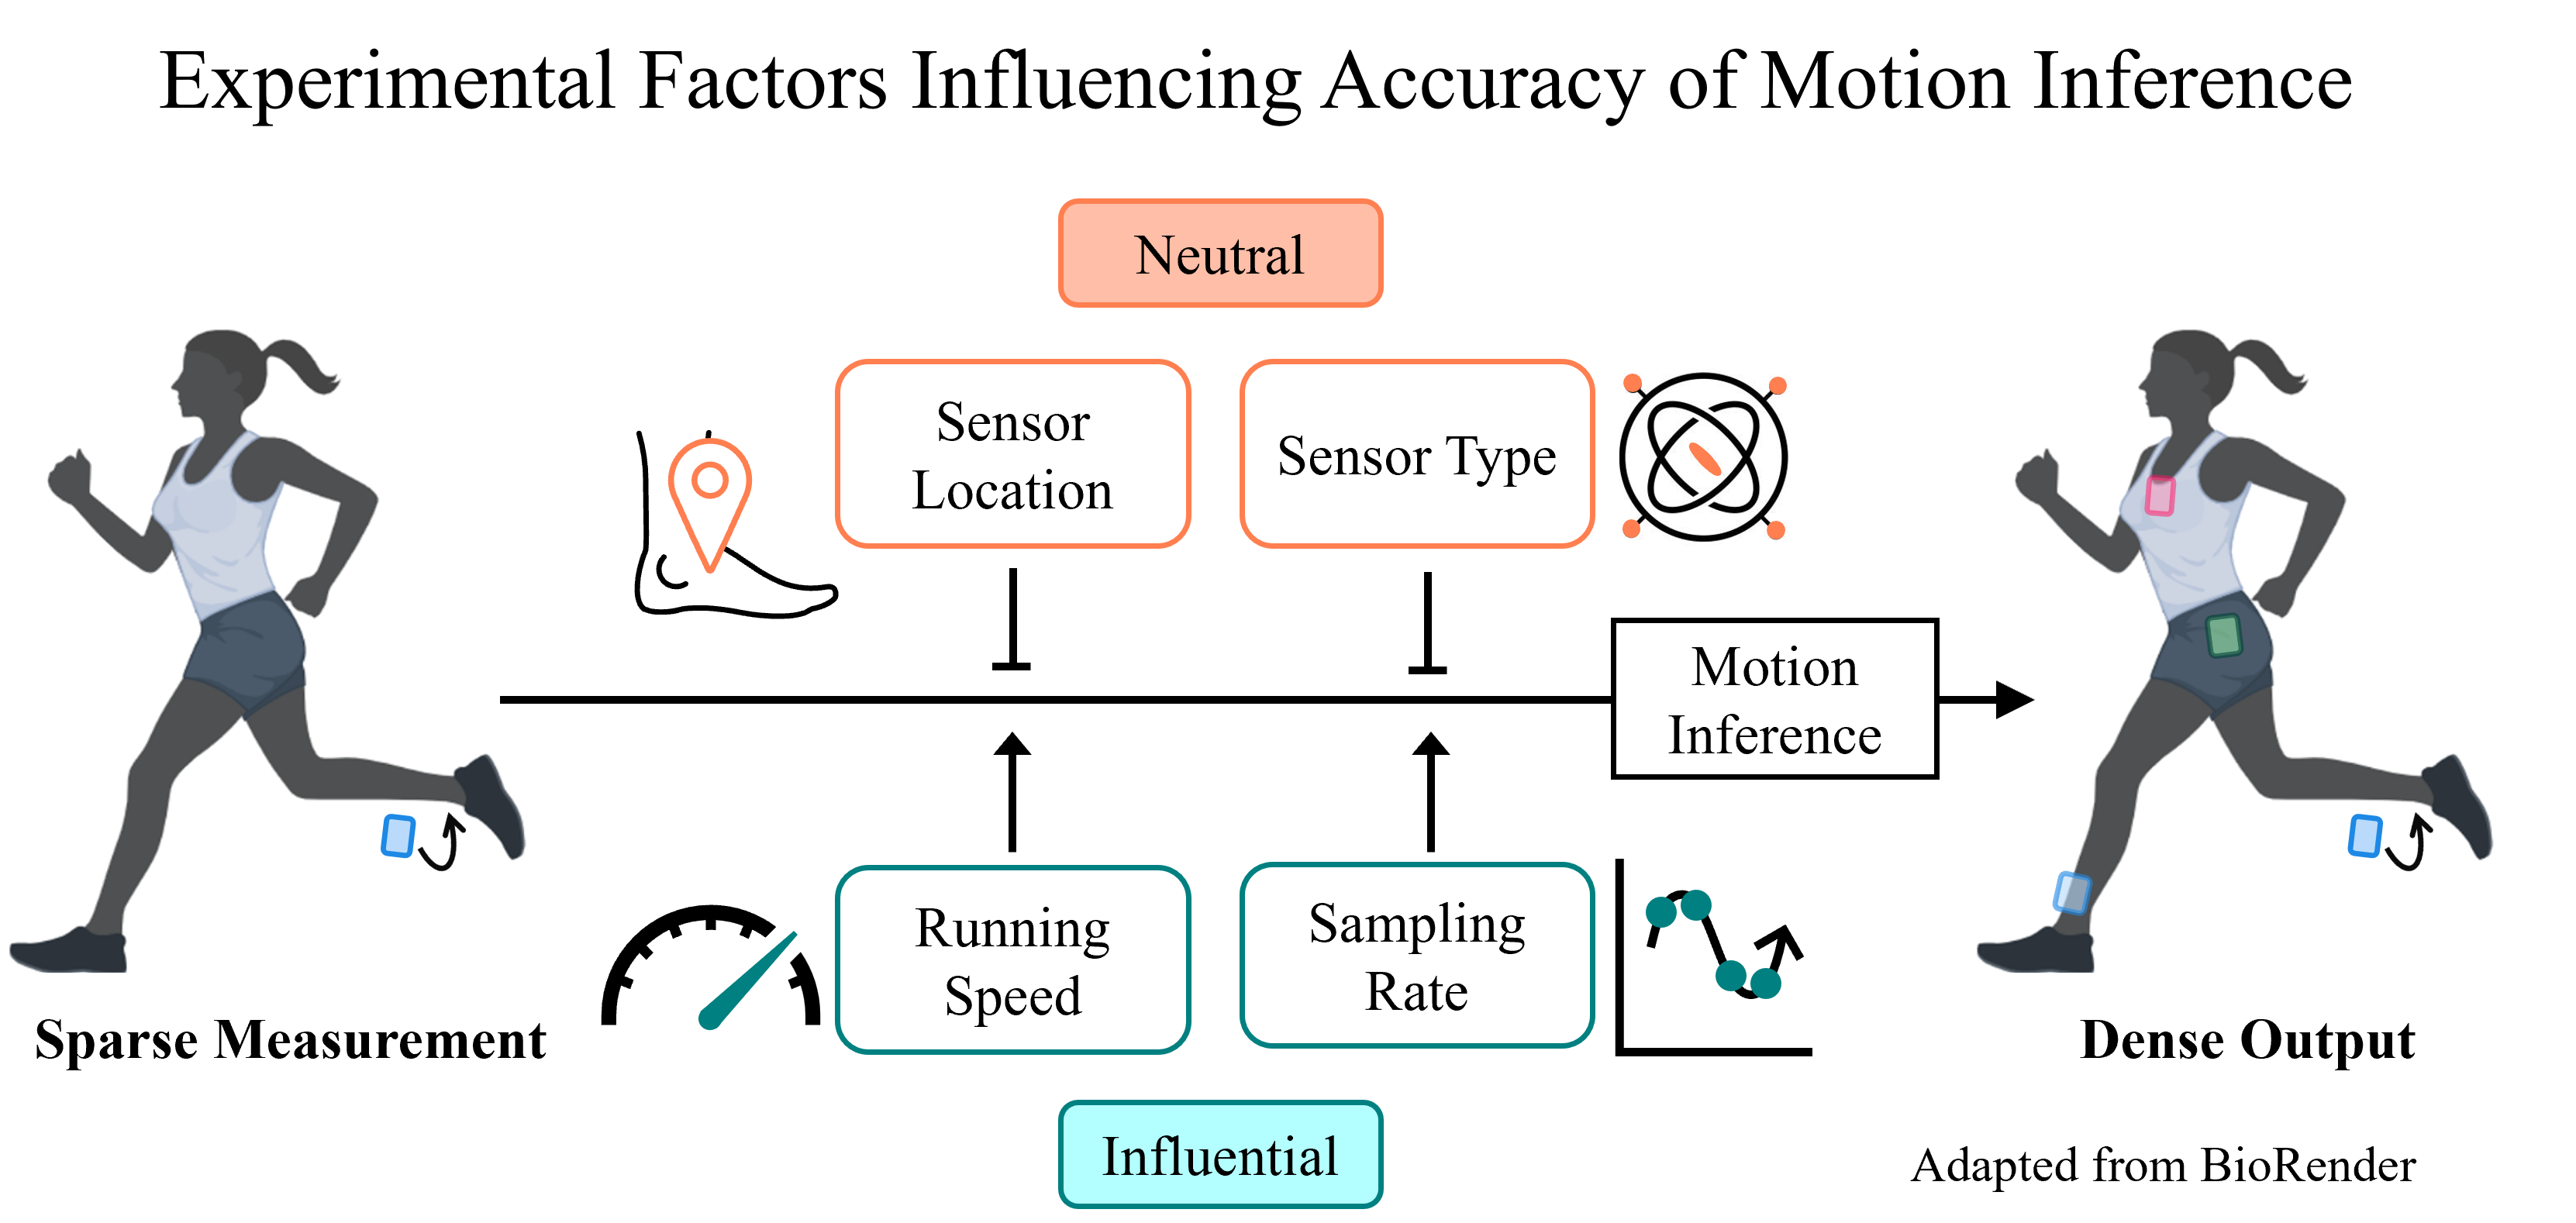
An illustration demonstrating experimental factors influencing the accuracy of motion inference when using Shallow recurrent decoder networks (SHRED) can reconstruct a dense set of time-series signals from a single input sensor. Running speed and sampling rate were most influential, while sensor location, and sensor type were neutral.Aim: Shallow recurrent decoder networks (SHRED) can reconstruct a dense set of time-series signals from a single input sensor and have been successful in human mobility applications, highlighting the potential for this algorithm to monitor running.

Methods: We trained and tested subject-specific SHRED models of nine subjects running on a treadmill to map from one input sensor to the remaining three IMUs. We varied the type of input to reflect experimental parameters that are important in running studies—sensor location, sensor type, sampling rate, and running speed—and compared the error of inferred signals from each input type.

Results: Sensor location and type did not impact SHRED inference accuracy, while decreasing the sampling rate affected the accuracy of ankle measurements. All ankle acceleration inferences from these models remained below the minimal detectable change threshold of 12.0 m/s2. SHRED models trained and tested at multiple speeds did not accurately infer IMU measurements below this threshold.

Interpretation: SHRED may broaden the scope of motion analysis by expanding access to data with fewer sensors. The data from this study and an instructional Jupyter notebook for training and testing individualized SHRED models are available at [link to GitHub].